
The Specific Cytochrome P450 Isoforms That Metabolize 75% of Prescription Drugs
While the human liver produces over 50 distinct cytochrome P450 enzymes, just two specific isoforms handle the metabolic breakdown of three-quarters of all prescription medications. Understanding this biological bottleneck explains why certain drug combinations cause severe side effects while others render treatments entirely ineffective.

- Clinical Pharmacologists
- Argue that routine pharmacogenomic testing for CYP450 variants should be mandatory before prescribing high-risk medications.
- Primary Care Physicians
- Emphasize the logistical barriers to universal genetic testing, relying instead on careful clinical monitoring and interaction-checking software.
- Integrative Medicine Practitioners
- Focus on the impact of diet, herbal supplements, and environmental toxins on CYP450 induction and inhibition.
Perspectives this story doesn't cover
- Patients experiencing adverse drug reactions
- Health insurance providers evaluating pharmacogenomic testing coverage
Key terms
- Cytochrome P450 (CYP450)
- A family of enzymes primarily found in the liver that oxidize foreign substances to help the body excrete them.
- Isoform
- A specific variant of a protein; in this case, the specific individual enzymes like CYP3A4 or CYP2D6 within the larger CYP450 family.
- Prodrug
- A medication that is biologically inactive when swallowed and must be metabolized by the body into its active form.
- Polymorphism
- A natural genetic variation that alters how an enzyme functions, leading to different metabolic speeds in different people.
Key points
- Over 50 cytochrome P450 enzymes exist in the human body, but just two handle nearly 75% of prescription drug metabolism.
- The CYP3A4 enzyme processes roughly half of all marketed drugs and is highly vulnerable to interference from foods like grapefruit.
- The CYP2D6 enzyme processes 20 to 25 percent of medications, but its efficiency is entirely dictated by a patient's genetics.
- Combining medications that use the same enzyme pathway can lead to dangerous toxic buildups or render treatments ineffective.
On August 1, 2007, the American Academy of Family Physicians published a clinical review noting a stark mathematical reality about human pharmacology: of the thousands of medications prescribed to patients, roughly 20 to 25 percent are processed by a single liver enzyme known as CYP2D6. When combined with another enzyme, CYP3A4, that share jumps to nearly 75 percent.[1][3]
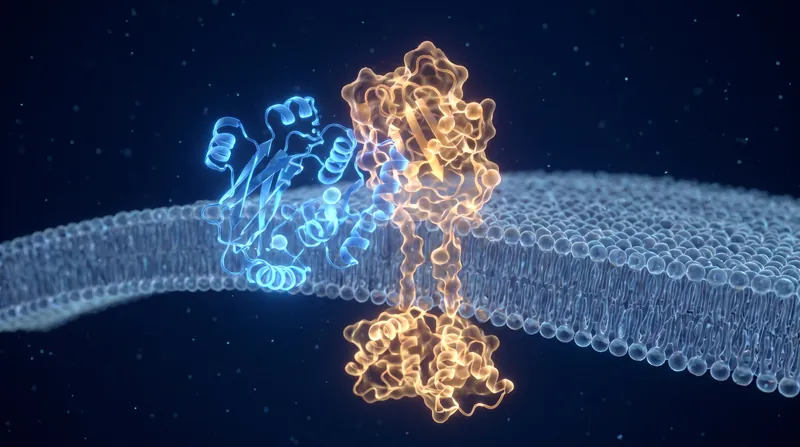
The human body expresses more than 50 distinct cytochrome P450 (CYP450) enzymes, a family of proteins responsible for breaking down foreign substances. Yet, the vast majority of the pharmaceutical burden falls on a remarkably small subset of these molecules.[8]
This concentration of metabolic labor creates a biological bottleneck. When a patient takes a statin for cholesterol, a selective serotonin reuptake inhibitor (SSRI) for depression, and a blood thinner for cardiovascular health, those molecules do not travel down separate, dedicated pathways. Often, they queue up for the exact same enzyme.[1]
The mechanism relies on oxidation. Cytochrome P450 enzymes, primarily located in the endoplasmic reticulum of liver cells, attach an oxygen atom to the drug molecule. This structural change typically makes the drug more water-soluble, allowing the kidneys to filter it out of the bloodstream and excrete it in urine.[8]
CYP3A4 is the undisputed workhorse of this system. According to Medsafe, the New Zealand Medicines and Medical Devices Safety Authority, CYP3A4 alone is responsible for metabolizing approximately 50 percent of all marketed drugs. It is highly concentrated in the liver and the small intestine, acting as the body's primary chemical defense line.[3]
Because CYP3A4 handles such a massive volume of traffic, it is highly susceptible to interference. Certain substances act as inhibitors, binding to the enzyme and blocking it from processing other drugs. Grapefruit juice is the most famous example; it contains furanocoumarins that irreversibly inhibit intestinal CYP3A4.[1][3]
If a patient consumes grapefruit juice while taking a medication metabolized by CYP3A4—such as the cholesterol-lowering drug atorvastatin—the drug cannot be broken down. It accumulates in the bloodstream, effectively turning a standard dose into a toxic overdose, which can lead to severe muscle breakdown.[3]
If a patient consumes grapefruit juice while taking a medication metabolized by CYP3A4—such as the cholesterol-lowering drug atorvastatin—the drug cannot be broken down.
Conversely, other substances act as inducers. St. John's wort, a common herbal supplement, accelerates the production of CYP3A4. If a patient taking oral contraceptives begins taking St. John's wort, the liver breaks down the contraceptive too quickly, dropping its concentration below the therapeutic threshold and risking an unintended pregnancy.[1][3]
The second major player, CYP2D6, presents a different clinical challenge: genetic variability. While CYP3A4 activity is largely influenced by external foods and drugs, CYP2D6 function is hardcoded into a patient's DNA.[2]
Research published in the International Journal of Molecular Sciences highlights that genetic polymorphisms in the CYP2D6 gene create four distinct patient profiles: poor metabolizers, intermediate metabolizers, extensive metabolizers, and ultrarapid metabolizers.[2]
This genetic variance has profound implications for pain management. Codeine is a prodrug; it is biologically inactive until CYP2D6 converts it into morphine. In a poor metabolizer, codeine provides zero pain relief. In an ultrarapid metabolizer, a standard dose is rapidly converted into a massive dose of morphine, risking fatal respiratory depression.[1][2]
The remaining metabolic workload is largely handled by four other isoforms: CYP2C9, CYP2C19, CYP1A2, and CYP2E1. CYP2C9 is particularly critical because it metabolizes warfarin, a blood thinner with a notoriously narrow therapeutic window.[2][8]
A 2025 analysis in Expert Opinion on Drug Metabolism & Toxicology emphasizes that as the global population ages and polypharmacy becomes the norm, understanding these pathways is no longer optional for prescribers. As researchers in Clinical Pharmacokinetics note, these enzymes "have multifarious influences on treatment outcomes," dictating whether a drug heals or harms.[4][5]
For patients, the practical takeaway is straightforward: the liver is not an infinite processing plant. Every new supplement, over-the-counter painkiller, or prescription medication is a new variable in a complex chemical equation.[7]
Pharmacogenomic testing—swabbing the cheek to map a patient's specific CYP450 genetic variants—is slowly moving from research labs into routine clinical practice, particularly in psychiatry and cardiology, to eliminate the trial-and-error approach to prescribing.[6][7]
The next phase of clinical integration relies on electronic health records automatically flagging these genetic bottlenecks. Until those systems are universally adopted, the most effective defense against adverse drug events remains a comprehensive pharmacy review, where a pharmacist runs a patient's entire medication list through a CYP450 interaction database before the first pill is swallowed.[7]
Sources
Source coverage
9 outlets
3 viewpoints surfaced







- [1]American Academy of Family PhysiciansPrimary Care Physicians
The Effect of Cytochrome P450 Metabolism on Drug Response, Interactions, and Adverse Effects
Read on American Academy of Family Physicians → - [2]International Journal of Molecular Sciences
Cytochrome P450 Enzymes and Drug Metabolism in Humans
Read on International Journal of Molecular Sciences → - [3]Medsafe
Drug Metabolism - The Importance of Cytochrome P450 3A4
Read on Medsafe → - [4]Expert Opinion on Drug Metabolism & ToxicologyClinical Pharmacologists
Insights into CYP450 polymorphisms and their impact on drug metabolism in Alzheimer's disease therapy
Read on Expert Opinion on Drug Metabolism & Toxicology → - [5]Clinical PharmacokineticsClinical Pharmacologists
Drug-Metabolizing Cytochrome P450 Enzymes Have Multifarious Influences on Treatment Outcomes
Read on Clinical Pharmacokinetics → - [6]IntechOpen
P450-Based Nano-Bio-Sensors for Personalized Medicine
Read on IntechOpen → - [7]Integrative Medicine: A Clinician's JournalIntegrative Medicine Practitioners
CYP450 Enzymes in Drug Metabolism and Personalized Medicine: A Narrative Review
Read on Integrative Medicine: A Clinician's Journal → - [8]StatPearls
Biochemistry, Cytochrome P450
Read on StatPearls → - [9]Factlen Editorial Team
Synthesis by Factlen editorial team
Read on Factlen Editorial Team →
Comments
More in Health
See all →Developmental Screening
The 75th Percentile Threshold: How the CDC Revised Developmental Milestones to Improve Early Screening
6 sources

Adaptogens
The Science of Ashwagandha: How the Ancient Adaptogen Rewires the Body's Stress Response
5 sources

Wastewater Surveillance
The Silent Radar: How Wastewater Surveillance Became Public Health's Ultimate Early Warning System
5 sources

Menopause Science
The New Consensus on Menopause Hormone Therapy: What the Latest Science Actually Says
5 sources

Every angle. Every day.
Get Health stories with full source coverage and perspective breakdowns delivered to your inbox.