
How Calcitonin Gene-Related Peptide (CGRP) Antagonists Block the Trigeminal Pathway to Abort Migraines
A new class of targeted therapies blocks the CGRP protein and its receptors in the trigeminal nerve system, offering the first preventive treatments specifically designed for migraine pathophysiology.
By Jun ZhaoEditorial desk byline — produced with AI under human editorial direction

Share this story
In short
- CGRP antagonists are the first class of medications developed specifically to prevent migraines by targeting their underlying biology.
- The therapies work by blocking the CGRP neuropeptide or its receptor, halting the inflammatory cascade in the trigeminal nerve.
- Monoclonal antibodies are administered via injection, while smaller-molecule gepants can be taken orally.
The historical standard for preventing a migraine relied on drugs engineered for entirely different conditions, forcing patients to use beta-blockers or anti-seizure medications that broadly depressed the central nervous system. Calcitonin gene-related peptide (CGRP) antagonists break from that legacy through sheer biological precision. Instead of altering systemic blood pressure or overall brain chemistry, these new therapies intercept the specific neuropeptide responsible for the migraine pain cascade, neutralizing the attack at its source while leaving the rest of the body's vascular network largely untouched.[6]
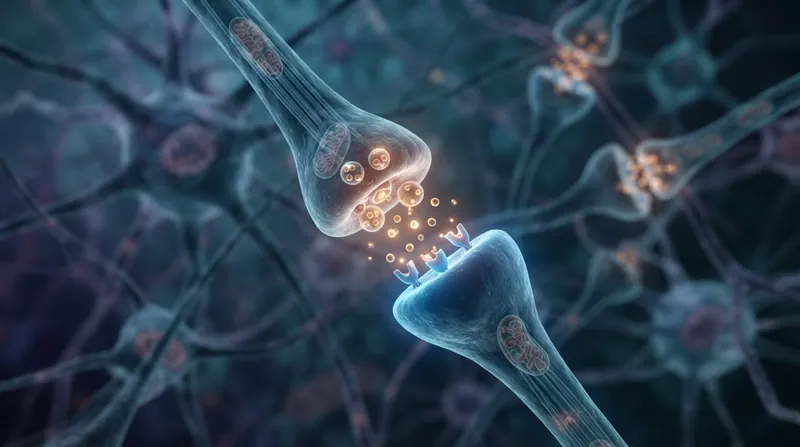
The biological mechanism centers on the trigeminal nerve, a major cranial nerve responsible for communicating pain, touch, and temperature sensitivities from the face and head to the brain. During a migraine attack, the trigeminal system releases a flood of CGRP, a 37-amino acid neuropeptide. This release initiates a localized inflammatory response in the meninges—the protective membranes covering the brain—and causes the surrounding cerebral blood vessels to dilate.[1][2][4][5]
"CGRP also causes inflammation and pain that happens during a migraine; it makes headache pain worse and causes headaches to last longer," notes WebMD's clinical overview, which highlights that individuals diagnosed with chronic migraines consistently show elevated levels of CGRP in their bloodstream. The American Migraine Foundation has consequently labeled the development of CGRP inhibitors "the biggest news in migraine treatment and prevention in decades."[6]
The pharmaceutical intervention works by physically blocking this pathway. The therapies are divided into two primary categories: large-molecule monoclonal antibodies and small-molecule receptor antagonists, known as gepants. Monoclonal antibodies, such as erenumab and fremanezumab, are engineered in a laboratory to bind directly to either the CGRP protein itself or its receptor. Because of their large molecular size, they do not cross the blood-brain barrier and must be administered via subcutaneous injection or intravenous infusion.[3][5][6]
In preclinical models, the efficacy of this blockade is highly measurable. A study published in the journal Molecules demonstrated that administering the anti-CGRP antibody fremanezumab significantly lowered the release of CGRP from the rat dura mater, the outermost layer of the meninges, effectively halting the localized blood flow increases that characterize the onset of a migraine. By preventing the neuropeptide from binding, the inflammatory cascade is aborted before the patient experiences the debilitating throbbing pain, photophobia, and nausea.[1][3]
The clinical results have fundamentally shifted the baseline expectations for the 39 million Americans living with the condition. In 2018, the U.S. Food and Drug Administration approved the first CGRP inhibitors for the prevention of episodic migraines—defined as up to 14 headache days per month—and chronic migraines, which involve 15 or more headache days per month. Clinical trials demonstrated that approximately one-third of patients experienced at least a 50 percent reduction in their monthly migraine days.[6]
The second category of CGRP antagonists, the small-molecule gepants, emerged shortly after. Unlike the injectable monoclonal antibodies, gepants like ubrogepant and rimegepant are taken orally and are small enough to penetrate the central nervous system rapidly. In 2021, the FDA expanded the approval of certain gepants to treat acute migraine attacks as they happen, providing an alternative to traditional triptans, which carry cardiovascular contraindications because they actively constrict blood vessels.[5][6]
Despite the robust clinical data, the evidence pack carries transparent limitations. CGRP is a potent vasodilator that plays a systemic role in regulating blood pressure and facilitating tissue repair.
While blocking it in the trigeminal system relieves head pain, the long-term cardiovascular safety of chronically suppressing a primary vasodilatory peptide remains under active surveillance, particularly for older adults or those with pre-existing vascular disease. Furthermore, the therapies do not achieve total remission for everyone; they are highly effective for a subset of patients, but others see only modest reductions in attack frequency.[2][5][6]
The clinical focus now shifts from proving efficacy to establishing long-term safety parameters. Because CGRP receptors are present throughout the cardiovascular system, the FDA and the European Medicines Agency are actively monitoring post-market data to determine if decades of continuous CGRP suppression will elevate the risk of ischemic events in aging patients. The defining metric for the drug class over the next five years will be whether those cardiovascular safety registries remain clear as the first cohort of patients enters their second decade of continuous therapy.[5][7]
Key terms
- Calcitonin Gene-Related Peptide (CGRP)
- A neuropeptide that transmits pain signals and causes blood vessels to dilate during a migraine attack.
- Trigeminal Nerve
- A major cranial nerve responsible for transmitting sensory information, including pain, from the face and head to the brain.
- Monoclonal Antibodies
- Laboratory-engineered proteins designed to bind to specific targets in the body, such as the CGRP molecule or its receptor.
- Gepants
- Small-molecule CGRP receptor antagonists that can be taken orally to block pain signals.
- Meninges
- The protective membranes that cover the brain and spinal cord, where migraine-related inflammation occurs.
Where opinion splits
Clinical Neurologists
View CGRP antagonists as a disease-specific breakthrough that avoids the systemic side effects of older off-label drugs.
For decades, neurologists had to rely on medications developed for hypertension, depression, or epilepsy to prevent migraines. These off-label treatments often caused systemic side effects like fatigue, weight gain, or cognitive fog, leading to high discontinuation rates. Clinical neurologists emphasize that CGRP antagonists finally provide a targeted tool that addresses the actual neurobiology of a migraine without broadly depressing the central nervous system.
Cardiovascular Safety Researchers
Urge caution regarding the long-term systemic effects of blocking a key vasodilatory peptide.
While the short-term safety profile of CGRP inhibitors is strong, cardiovascular researchers point out that CGRP plays a crucial protective role during ischemic events, such as a heart attack or stroke, by dilating blood vessels to improve blood flow. There is ongoing debate about whether chronically blocking this peptide could remove a vital physiological safety net, particularly in older patients or those with pre-existing vascular disease.
Patient Advocates
Celebrate the quality-of-life improvements while highlighting the ongoing challenges of drug cost and insurance access.
For patients who have spent years cycling through ineffective treatments, the introduction of CGRP antagonists has been life-altering, allowing many to return to work and daily activities. However, patient advocacy groups consistently highlight that the high out-of-pocket costs and stringent insurance prior-authorization requirements—often mandating that patients fail multiple older, cheaper drugs first—create significant barriers to access for those who need the medication most.
- Clinical Neurologists
- View CGRP antagonists as a long-overdue, disease-specific breakthrough that fundamentally changes migraine management.
- Patient Advocates
- Celebrate the quality-of-life improvements while highlighting the ongoing challenges of drug cost and insurance access.
- Cardiovascular Safety Researchers
- Urge caution regarding the long-term systemic effects of blocking a key vasodilatory peptide, particularly in vulnerable populations.
Perspectives this story doesn't cover
- Health Insurance Providers
- Pediatric Neurologists
Sources
Source coverage
7 outlets
3 viewpoints surfaced





- [1]Headache: The Journal of Head and Face PainClinical Neurologists
CGRP and the Trigeminal System in Migraine
Read on Headache: The Journal of Head and Face Pain → - [2]Headache: The Journal of Head and Face PainClinical Neurologists
The Trigeminovascular Pathway: Role of CGRP and CGRP Receptors in Migraine
Read on Headache: The Journal of Head and Face Pain → - [3]MoleculesCardiovascular Safety Researchers
The Anti-CGRP Antibody Fremanezumab Lowers CGRP Release from Rat Dura Mater and Meningeal Blood Flow
Read on Molecules → - [4]Headache
Two Mechanisms Involved in Trigeminal CGRP Release: Implications for Migraine Treatment
Read on Headache → - [5]Current Neurology and Neuroscience ReportsCardiovascular Safety Researchers
CGRP mechanism antagonists and migraine management
Read on Current Neurology and Neuroscience Reports → - [6]WebMDClinical Neurologists
What Are CGRP Inhibitors for Migraine?
Read on WebMD → - [7]Factlen Editorial TeamPatient Advocates
Synthesis by Factlen editorial team
Read on Factlen Editorial Team →

More in Health
See all →Memory Distrust
Conceptual Familiarity Erodes Memory Vividness: Why Repeated Checking Deepens Doubt in OCD
5 sources

ADHD Neurobiology
How Stimulants Calm ADHD by Tuning Prefrontal Receptors to Boost Signal-to-Noise Ratios
5 sources
Anxiety Symptoms
How Hyperventilation Traps Calcium to Cause Tingling During Panic Attacks
4 sources

Antidepressant Deprescribing
Hyperbolic Serotonin Transporter Saturation Concentrates Most Withdrawal in the Final Milligrams of Antidepressant Deprescribing
11 sources

Comments
Every angle. Every day.
Get Health stories with full source coverage and perspective breakdowns, free every day.