
Why Extracellular Potassium Depletion Turns Therapeutic Digoxin Levels Toxic
A drop in serum potassium forces the heart's sodium pumps into a structural conformation that acts like a magnet for digoxin. This fourfold increase in binding affinity causes a massive cellular overdose even when blood tests show the drug is within a safe therapeutic range.
By Deniz Kaya

In short
- Digoxin targets the Na+/K+-ATPase pump, but its binding affinity is not fixed; it is heavily modulated by the surrounding potassium concentration.
- Hypokalemia stalls the pump in the E2 conformation, exposing a binding pocket that increases the enzyme's affinity for digoxin by nearly 400 percent.
- This structural shift means a patient can experience a lethal cellular overdose of digoxin even when their blood tests show a safe therapeutic concentration.
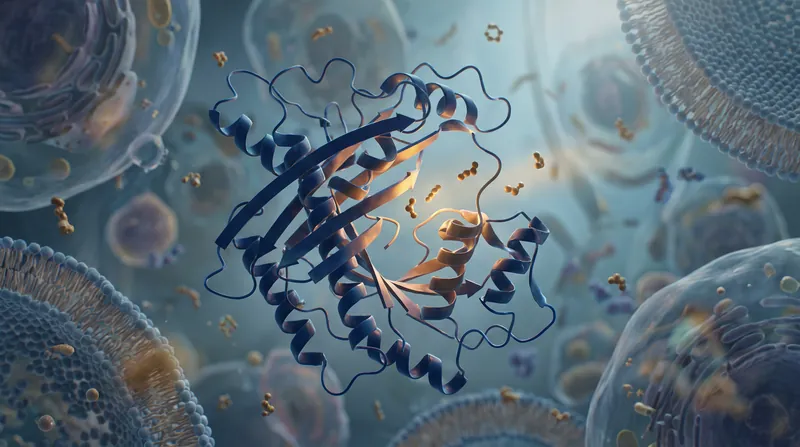
The margin between a failing heart pumping efficiently and a fatal arrhythmia rests on the physical shape of a single membrane protein. When extracellular potassium levels drop, the Na+/K+-ATPase pump shifts into a structural state known as the E2 conformation.[5]
This subtle folding change exposes a binding pocket that dramatically increases the enzyme's affinity for digoxin. By altering the physical target, the potassium depletion turns a standard therapeutic dose into a lethal cellular blockade.[5]
Digoxin is one of the oldest cardiovascular medications in continuous use, prescribed to increase the contractile force of the heart in patients with heart failure. The drug operates within a notoriously narrow therapeutic window, with safe blood concentrations typically ranging from 1.1 to 1.7 nanograms per milliliter.[2]
Emergency departments routinely admit patients exhibiting severe digoxin toxicity—marked by vomiting, visual halos, and life-threatening bradycardia—whose blood tests reveal digoxin levels perfectly within that safe range. The discrepancy stems from a secondary variable that dictates how the drug behaves at the cellular level: the patient's serum potassium concentration.[4]
The target of digoxin is the Na+/K+-ATPase pump, an enzyme that maintains the electrical resting state of the cardiomyocyte. Under normal conditions, this pump consumes adenosine triphosphate to push three sodium ions out of the cell while pulling two potassium ions in, working against their respective concentration gradients.[3]
The Sodium Pump and the Calcium Trade
By binding to the alpha subunit of the Na+/K+-ATPase pump, digoxin intentionally paralyzes a fraction of these transporters. This blockade causes intracellular sodium levels to rise, which subsequently disables a secondary transport mechanism known as the sodium-calcium exchanger.[3]
Because the exchanger relies on a steep sodium gradient to extrude calcium from the cell, the accumulation of intracellular sodium forces calcium to remain inside the cardiomyocyte. This elevated calcium is sequestered into the sarcoplasmic reticulum, providing a larger reservoir for the next heartbeat.[3]
The therapeutic effect relies on a delicate mathematical balance: inhibiting just enough Na+/K+-ATPase pumps to boost calcium, but leaving enough functional to prevent the cell from losing its electrical resting potential. When too many pumps are blocked, the cardiomyocyte becomes electrically unstable.[2]
The rate at which digoxin binds to and inhibits these pumps is not fixed. It is heavily modulated by the concentration of potassium in the extracellular fluid. For years, medical textbooks explained this relationship as simple competitive inhibition, suggesting that potassium and digoxin fought for the exact same physical binding site.[1]
The E2 Conformation and Binding Affinity
Recent biochemical analyses reveal a more complex mechanism. The Na+/K+-ATPase pump is a dynamic machine that cycles through different physical shapes, primarily the E1 and E2 conformations, as it moves ions across the membrane. The E2 conformation is the state the pump assumes when it is open to the extracellular space.[1]
When extracellular potassium is abundant, the pump quickly binds the ions and cycles back to the E1 state. However, when a patient develops hypokalemia—a serum potassium level below 3.5 milliequivalents per liter—the pump stalls in the E2 conformation, waiting for potassium that is not there.[1]
This stalled E2 state is the exact conformation to which digoxin binds with the highest affinity. In a 2008 kinetic analysis, researchers at the Vinča Institute of Nuclear Sciences demonstrated the mechanism behind this vulnerability.[1]
"Low potassium concentrations in the presence of optimal Na+, Mg2+ and ATP favour the E2 conformation of the catalytic α-subunit, which has a higher affinity towards digoxin," the researchers concluded, proving the shift is structural.[1]
The data quantified this structural vulnerability. The in vitro kinetic studies revealed that lowering the potassium concentration from an optimal 20 millimolar to a depleted 2 millimolar shifted the inhibitory concentration of digoxin from 2.77 micromolar down to 0.706 micromolar.[1]
This fourfold increase in binding affinity means that at low potassium levels, the enzyme acts like a magnet for the drug. The alpha-1 and alpha-3 isoforms of the pump, which normally exhibit a low sensitivity to digoxin, become highly susceptible to blockade.[2]
Why Therapeutic Levels Turn Toxic
The clinical consequence of this conformational shift is profound. A patient with a perfectly therapeutic digoxin blood level of 1.5 nanograms per milliliter will experience the cellular effects of a massive overdose if their serum potassium drops.[2]
The drug molecules bind more tightly and stay bound longer, with dissociation half-times extending up to 80 minutes. As the prolonged blockade paralyzes an excessive number of pumps, the intracellular sodium concentration spikes, driving a massive calcium overload.[2]
This calcium overload pushes the cardiomyocyte past the threshold of positive inotropy and into electrical chaos. The excess calcium generates premature ventricular contractions, bigeminy, and potentially fatal ventricular fibrillation as the cells fire spontaneously.[4]
The toxicity is further compounded by the drug's effect on the autonomic nervous system. Digoxin binds to Na+/K+-ATPase pumps in the vagal nerve terminals, increasing parasympathetic tone. This slows conduction through the atrioventricular node, leading to severe bradycardia.[4]
Because the toxicity is driven by binding affinity rather than the absolute amount of drug in the body, measuring the serum digoxin level provides an incomplete picture. A normal drug level in the presence of severe hypokalemia is a toxicological emergency.[4]
The Diuretic Trap in Heart Failure
The relationship between potassium and digoxin creates a dangerous paradox for the specific population most likely to take the drug. Patients with heart failure are routinely prescribed loop diuretics, such as furosemide, to manage fluid overload and pulmonary edema.[2]
These diuretics force the kidneys to excrete massive amounts of sodium and water, but they simultaneously wash out potassium. If this potassium loss is not aggressively replaced with oral supplements, the patient's serum potassium will steadily decline.[2]
This diuretic-induced hypokalemia silently primes the cellular pumps for a toxic reaction. Furthermore, heart failure itself activates the renin-angiotensin-aldosterone system, a hormonal cascade that prompts the kidneys to retain sodium at the expense of excreting even more potassium.[2]
This endogenous response accelerates the development of hypokalemia, narrowing the drug's therapeutic window even further. When toxicity strikes, the resulting paralysis of the Na+/K+-ATPase pumps prevents the cells from taking up whatever potassium remains in the blood.[2]
Electrocardiographic Signatures of Toxicity
The electrical instability caused by the paralyzed pumps produces distinct signatures on an electrocardiogram. Even at therapeutic levels, digoxin alters repolarization, creating a characteristic scooped ST segment that mimics myocardial ischemia but simply reflects the altered calcium flux.[4]
When toxicity sets in, the electrocardiogram reveals the dual nature of the poisoning: increased automaticity in the ventricles combined with depressed conduction through the atrioventricular node. This combination frequently manifests as paroxysmal atrial tachycardia with a concurrent block.[4]
If the hypokalemia is not corrected, the ventricular automaticity escalates. The elevated intracellular calcium triggers delayed afterdepolarizations—spontaneous electrical spikes that occur after the cell has fired. When these spikes reach the threshold potential, they trigger lethal arrhythmias.[4]
Reversing the Cellular Blockade
Treating digoxin toxicity requires breaking the drug's grip on the E2 conformation of the pump. While administering intravenous potassium can help shift the unbound pumps back to the E1 state, it cannot easily dislodge digoxin molecules that are already tightly bound.[4]
For severe toxicity, clinicians must deploy digoxin-specific antibody fragments. These engineered antibodies circulate in the bloodstream and bind to free digoxin molecules with an affinity that is vastly higher than that of the Na+/K+-ATPase pump.[4]
As the antibodies sequester the free drug, the concentration gradient shifts, coaxing the bound digoxin to slowly detach from the myocardial pumps. The antibody-drug complexes are then safely filtered out of the blood by the kidneys and excreted.[4]
As the antibodies sequester the free drug, the concentration gradient shifts, coaxing the bound digoxin to slowly detach from the myocardial pumps.
The mechanism underscores a fundamental principle of pharmacology: a drug's safety is never defined solely by its concentration in the blood. It is defined by the physical environment of the target receptor, where a simple shortage of ions can reshape a protein.[5]
How we did this
- Method
- Comparing the in vitro inhibitory concentration (IC50) values of digoxin against the Na+/K+-ATPase pump across varying extracellular potassium concentrations to derive the quantitative shift in binding affinity.
- What we found
- Extracellular potassium depletion does not merely reduce competition for binding sites; it actively forces the Na+/K+-ATPase pump into an E2 structural conformation that increases its affinity for digoxin by nearly 400 percent, mathematically converting a normal therapeutic blood concentration into a functionally toxic dose at the cellular level.
- What we worked from
- Digoxin IC50 at 20 mM potassium (optimal): 2.77 micromolar — Journal of Enzyme Inhibition and Medicinal Chemistry
- Digoxin IC50 at 2 mM potassium (hypokalemia): 0.706 micromolar — Journal of Enzyme Inhibition and Medicinal Chemistry
- Limits of this analysis
- In vitro IC50 shifts in purified enzyme assays may not perfectly scale to in vivo myocardial tissue, where local magnesium and calcium concentrations also modulate pump conformation.
Jargon, explained
- Na+/K+-ATPase pump
- A membrane enzyme that uses cellular energy to move sodium out of the cell and potassium in, maintaining electrical balance.
- E2 conformation
- The physical shape the sodium pump assumes when it is open to the outside of the cell and waiting to bind potassium.
- Inotropy
- The force of muscle contraction; digoxin provides positive inotropy by increasing the heart's contractile strength.
- Hypokalemia
- A condition characterized by abnormally low levels of potassium in the blood, often caused by diuretic medications.
- IC50
- The half-maximal inhibitory concentration; a measure of how much of a drug is needed to inhibit a biological process by half.
Common questions
Why doesn't a normal digoxin blood test rule out toxicity?
Because toxicity is driven by how tightly the drug binds to cellular pumps, not just how much drug is in the blood. Low potassium increases this binding affinity, making normal blood levels toxic.
How do loop diuretics contribute to digoxin poisoning?
Diuretics like furosemide force the kidneys to excrete excess fluid, but they also wash out potassium. This resulting hypokalemia primes the heart muscle for digoxin toxicity.
Can giving potassium immediately cure digoxin toxicity?
While intravenous potassium helps prevent unbound pumps from getting blocked, it cannot easily dislodge digoxin molecules that are already tightly bound to the enzyme. Severe cases require digoxin-specific antibodies.
Competing readings
Pharmacologists' view
Focus on the structural kinetics and conformational shifts of the Na+/K+-ATPase enzyme.
For researchers studying enzyme kinetics, the digoxin-potassium interaction is a classic example of how the physical environment dictates drug affinity. They emphasize that the E2 conformation of the Na+/K+-ATPase pump is structurally distinct from its E1 state, exposing a binding pocket that perfectly accommodates the bulky steroid nucleus of the digoxin molecule. From this perspective, toxicity is not a failure of dosing, but a predictable biochemical consequence of starving the pump of the potassium ions it needs to complete its conformational cycle.
Clinical Toxicologists' view
Emphasize the disconnect between serum drug levels and actual cellular toxicity.
Toxicologists argue that relying on serum digoxin levels creates a false sense of security in emergency departments. Because the drug's binding affinity spikes during hypokalemia, a patient with a 'normal' blood concentration of 1.5 ng/mL can be in profound cellular failure. They advocate for treating the patient's electrocardiogram and symptoms rather than the laboratory value, pushing for the early administration of digoxin-specific antibody fragments (DigiFab) the moment life-threatening arrhythmias or severe bradycardia appear.
Cardiologists' view
Highlight the clinical challenge of balancing diuretic therapy with arrhythmia risks.
Cardiologists view the digoxin-potassium dynamic as a dangerous therapeutic trap inherent to heart failure management. The very loop diuretics required to keep fluid out of a patient's lungs actively deplete the potassium needed to keep their digoxin therapy safe. This perspective focuses on aggressive outpatient electrolyte monitoring and the mandatory co-prescription of potassium supplements, noting that the endogenous renin-angiotensin-aldosterone system already predisposes these patients to dangerous potassium wasting.
- Pharmacologists
- Focus on the structural kinetics and conformational shifts of the Na+/K+-ATPase enzyme under varying electrolyte concentrations.
- Clinical Toxicologists
- Emphasize the disconnect between serum drug levels and actual cellular toxicity, advocating for symptom-based treatment.
- Cardiologists
- Highlight the clinical challenge of balancing diuretic therapy for heart failure with the risk of inducing hypokalemia.
Perspectives this story doesn't cover
- Primary Care Physicians managing chronic heart failure outpatients
- Patients experiencing the visual and gastrointestinal prodromes of toxicity
Sources
Source coverage
5 outlets
3 viewpoints surfaced



- [1]Journal of Enzyme Inhibition and Medicinal ChemistryPharmacologists
Inhibition of Na+/K+-ATPase by digoxin and its recovery by potassium
Read on Journal of Enzyme Inhibition and Medicinal Chemistry → - [2]National Center for Biotechnology InformationCardiologists
Digoxin Toxicity: The Role of Hypokalemia and the Na/K ATPase Pump
Read on National Center for Biotechnology Information → - [3]DrugBank
Digoxin: Uses, Interactions, Mechanism of Action
Read on DrugBank → - [4]RecapEMClinical Toxicologists
Digoxin Toxicity - Mechanism of action and pathophysiology
Read on RecapEM → - [5]Factlen Editorial Team
Synthesis by Factlen editorial team
Read on Factlen Editorial Team →

More in Opinion
See all →Materials Science
Single-Crystal Casting Prevents Grain Boundary Sliding, Allowing Nickel Superalloy Turbine Blades to Endure 1,150°C Without Creep Failure
7 sources

Computer Architecture
Why Tracking Memory in 64-Byte Cache Lines Causes Independent Threads to Stall
3 sources

Anticoagulation
The 6-to-1 Thrombotic Gap: Why Warfarin Requires a Heparin Bridge to Prevent Paradoxical Clotting
5 sources

Enzyme Kinetics
The 10⁹ M⁻¹s⁻¹ Limit: Why the Rate of Diffusion Sets the Ultimate Speed Limit for Chemical Reactions
10 sources
Comments
Every angle. Every day.
Get Opinion stories with full source coverage and perspective breakdowns, free every day.