
British Healthcare Worker Evacuated to UK After Contracting Ebola in DR Congo
A British doctor infected with the Bundibugyo strain of Ebola has been medically evacuated to London's Royal Free Hospital. The infection occurred during the patient's deployment to the Democratic Republic of the Congo, where an unprecedented outbreak has claimed over 5,100 lives.
By Maya Khalil

Share this story
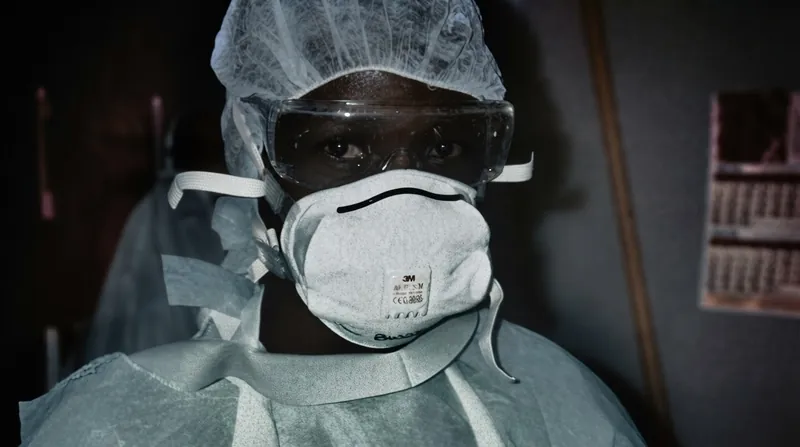
A British healthcare worker who contracted the Bundibugyo strain of Ebola while responding to the unprecedented epidemic in the Democratic Republic of the Congo has been medically evacuated to London. The patient arrived in the United Kingdom on Thursday, November 5, 2026, aboard a specialized medical transport.[2][3][4]
The evacuation marks the first time a British national has been infected during the current outbreak, which has rapidly become the second largest in recorded history. The worker was deployed by a humanitarian organization to assist in containing the virus in the DRC.[3][4]
Their identity has not been disclosed to protect patient confidentiality during their treatment. They are now receiving care in a high-level isolation unit at the Royal Free Hospital in Hampstead, north London.[3][4]
“UKHSA and the NHS have well-established and robust infection prevention and control protocols to limit the risk of onward transmission,” said Dr. Renu Bindra, deputy director for all-hazards public health response at the UK Health Security Agency.[3][4]
Dr. Bindra emphasized that the specialized facilities in London are designed for exactly this scenario. “The risk to the wider public remains low,” she added, noting that the Royal Free Hospital has successfully treated Ebola patients during previous international outbreaks without any domestic spread.[3][4]
A rapidly expanding epidemic
The ongoing epidemic in the DRC, officially declared in May 2026, has overwhelmed local health infrastructure. As of early November, the outbreak has infected more than 10,600 people, with over 5,100 related deaths.[4]
The geographic footprint of the virus has expanded dramatically over the past six months. When the outbreak was first identified, it was confined to just three health zones in the eastern DRC. Today, the pathogen has spread to 67 distinct health zones across eight provinces.[4]
Unlike the Zaire ebolavirus responsible for the devastating 2014 West African epidemic, this outbreak is driven by the Bundibugyo virus. The distinction is critical because existing stockpiles of Ebola vaccines and monoclonal antibody treatments were developed specifically for the Zaire strain.[3]
Ebola does not spread through the air like respiratory viruses such as influenza or COVID-19. Transmission requires direct contact with the bodily fluids—such as blood, sweat, or vomit—of an infected person who is actively showing symptoms.[3]
“The infection of a British healthcare worker with Ebola is deeply concerning, but it is not entirely unexpected,” said Dr. Damien Tully, an infectious disease expert at the London School of Hygiene & Tropical Medicine.[4]
“Healthcare workers are on the front line of these outbreaks, often treating severely ill patients under extremely challenging conditions,” Dr. Tully explained. “Even with rigorous protective measures, accidental exposures can occur.”[4]
The European medical response
Medical evacuations for highly infectious pathogens require immense logistical coordination. The transfer was jointly arranged by the British and Congolese governments, alongside international health partners, ensuring the patient remained completely isolated during the flight and subsequent ambulance transfer.[4]
The Royal Free Hospital is uniquely equipped for this crisis. Its high-level isolation unit features specialized ventilation systems, dedicated laboratories, and strict access controls that operate entirely separate from the rest of the hospital.[3][4]
Between 2014 and 2015, the facility successfully treated multiple British healthcare workers evacuated from West Africa. All of those patients survived their infections, and there was zero onward transmission within the UK, providing a proven blueprint for managing the current patient's care.[4]
This patient is the third European to test positive and return home during the 2026 outbreak. In June, France confirmed a case in a doctor returning from a humanitarian mission in the DRC, who has since fully recovered.[4]
Last month, a Swiss woman who contracted the virus in Uganda was medically evacuated to Geneva for intensive treatment, while her husband was held in isolation in Zurich as a precaution.[4]
While international evacuations draw significant attention, the primary crisis remains concentrated in Central and East Africa. The virus has repeatedly crossed international borders, with Kenya and Nigeria reporting imported cases in October 2026.[3]
Managing the frontline risks
The infection of international medical staff highlights the severe occupational hazards inherent in outbreak response. Local Congolese healthcare workers bear the heaviest burden, facing extreme fatigue, resource shortages, and the constant psychological stress of operating in high-mortality environments.[4]
Maintaining perfect infection control in resource-limited settings is notoriously difficult. Protective suits are sweltering in the tropical heat, limiting the amount of time staff can safely spend inside treatment zones, and a single breach in protocol can result in viral exposure.[4]
British health officials are working proactively to reassure the public that the virus poses no threat to the general population. Because Ebola patients are not infectious during the two-to-21-day incubation period, the risk of a community outbreak in London is effectively zero.[3]
However, the incident underscores the interconnected nature of global health security. Dr. Jean Kaseya, director general of the Africa Centres for Disease Control and Prevention, recently warned that the “unprecedented” spread of the Bundibugyo strain means no continent is entirely insulated.[3]
The clinical path forward
At the Royal Free Hospital, the evacuated worker will receive round-the-clock supportive care. This typically involves intravenous fluids, electrolyte balancing, and careful management of oxygen status and blood pressure to support the body's natural immune response.[3][4]
Authorities are currently monitoring anyone who may have had unprotected contact with the worker before their diagnosis. In the DRC, contact tracing remains a monumental challenge, with thousands of individuals requiring daily monitoring to quickly isolate new infections.[3]
The evacuation amplifies the urgent need for effective medical countermeasures. Experimental vaccine trials are currently under way in the region, but until they prove effective and can be deployed at scale, the outbreak response will continue to rely on traditional containment strategies.[3]
Key points
- A British healthcare worker infected with Ebola in the DRC was medically evacuated to London on November 5, 2026.
- The patient is receiving specialized care in a high-level isolation unit at the Royal Free Hospital.
- The ongoing DRC epidemic, driven by the Bundibugyo strain, has infected over 10,600 people and caused more than 5,100 deaths.
- UK health officials emphasize that robust infection control protocols are in place and the risk to the wider public remains low.
Unanswered questions
- The specific circumstances of how the healthcare worker was exposed to the virus despite utilizing protective equipment.
- How the patient's immune system will respond to the Bundibugyo strain, which currently lacks approved antiviral treatments.
- Whether the ongoing vaccine trials in the DRC will yield an effective countermeasure in time to curb the epidemic's current trajectory.
How we got here
May 2026
The DRC health ministry officially declares an outbreak of the Bundibugyo ebolavirus in the country's eastern provinces.
June 2026
France confirms an imported case in a doctor returning from a humanitarian mission in the DRC.
October 2026
Kenya and Nigeria report imported cases, while a Swiss woman infected in Uganda is evacuated to Geneva.
November 4, 2026
The UK government confirms a British national has tested positive for Ebola in the DRC and initiates evacuation protocols.
November 5, 2026
The patient arrives in London and is transferred to the Royal Free Hospital's high-level isolation unit.
- UK Health Authorities
- Focused on domestic containment and reassuring the public about the low risk of local transmission.
- Frontline Medical Experts
- Emphasize the severe occupational hazards and challenging conditions faced by outbreak responders.
- Global Health Leadership
- Warn that the epidemic's unprecedented scale requires heightened international preparedness.
Perspectives this story doesn't cover
- Local Congolese healthcare workers managing the bulk of the epidemic
- The humanitarian organization that deployed the evacuated worker
Sources
Source coverage
5 outlets
3 viewpoints surfaced





- [1]Reuters
British healthcare worker with Ebola to be evacuated from Congo to UK, document shows
Read on Reuters → - [2]BBC NewsUK Health Authorities
British man infected with Ebola in DR Congo to be flown back to UK
Read on BBC News → - [3]The GuardianGlobal Health Leadership
British healthcare worker with Ebola evacuated from DR Congo to UK
Read on The Guardian → - [4]AP NewsFrontline Medical Experts
British doctor with Ebola evacuated to London from Congo
Read on AP News → - [5]The BMJ
Ebola UK: British person infected in DRC outbreak will be evacuated home
Read on The BMJ →

More in Health
See all →Ebola Epidemic
DRC Ebola Outbreak Surpasses 10,000 Cases as Bundibugyo Strain Spreads Without Approved Vaccine
6 sources
Immunization Gaps
Global Measles Cases Surge 40 Percent as Post-Pandemic Childhood Vaccination Rates Plummet
6 sources

Climate Mortality
Record European Heatwaves Caused Over 50,000 Urban Deaths in Summer 2026
4 sources

Health Inequality
WHO Report Identifies Socioeconomic Disparities as Dominant Contributor to Chronic Disease Burdens
5 sources

Comments
Every angle. Every day.
Get Health stories with full source coverage and perspective breakdowns, free every day.